
Your gift is 100% tax deductible.
Kidney Cancer Stages and Prognostic Factors
If you are diagnosed with kidney cancer, your cancer care team will try to figure out if it has spread, and if so, how far. This process is called staging.
The stage of your cancer describes the cancer’s location and how much cancer is in your body. It helps determine how serious the cancer is and how best to treat it. Doctors also use a cancer's stage when talking about survival statistics.
Doctors can also use other factors to help them understand your prognosis (outlook). These are called prognostic factors. They can include certain tests, your overall health, and other information. Doctors look at the stage of your cancer along with these prognostic factors when they consider your outlook and treatment options.
For information on Wilms tumor, a kidney cancer of childhood, see Wilms Tumor Stages and Risk Groups.
How is kidney cancer staged?
The stages of kidney cancer range from I through IV.
- The lower the number, the less the cancer has spread.
- A higher number, such as stage IV, means cancer has spread more.
Although other factors can also be important, cancers with similar stages tend to have a similar outlook and are often treated in much the same way.
Clinical vs. pathological stage
The stage of a kidney cancer can be determined in 2 ways:
The clinical stage is based on the results of physical exams, imaging tests, and any biopsies. The clinical stage can be helpful in determining treatment options.
If you have surgery, doctors will also assign your cancer a pathological stage (surgical stage). This is partly based on the information used for the clinical stage. But it is also based on any information doctors learn about your cancer when they look at the tissue they removed during surgery.
The clinical stage and pathological stage use the same numbered staging system outlined below. But it’s important to know that your stage number might change after you have surgery.
For example, surgery might show that the cancer has spread farther than what was seen on imaging tests. If this is the case, the pathological stage might be higher than the clinical stage.
AJCC TNM staging system
The staging system most often used for kidney cancer is the American Joint Committee on Cancer (AJCC) TNM system.
The TNM system is based on 3 key pieces of information:
- Size and extent of the primary tumor (T): How large is the primary (main) tumor? Has it grown into nearby areas?
- Spread to nearby lymph nodes (N): Has the cancer spread to nearby lymph nodes?
- Spread (metastasis) to distant sites (M): Has the cancer spread to other organs such as the bones, brain, or lungs?
Numbers or letters: Numbers or letters after T, N, and M give more detail about each of these factors. Higher numbers mean the cancer is more advanced.
Stage grouping: After a person’s T, N, and M categories are determined, this information is combined and an overall stage is assigned. This process is called stage grouping. To learn more, see Cancer Staging.
Kidney cancer staging can be complex. If you have any questions about your stage, please ask your cancer care team to explain it in a way you understand.
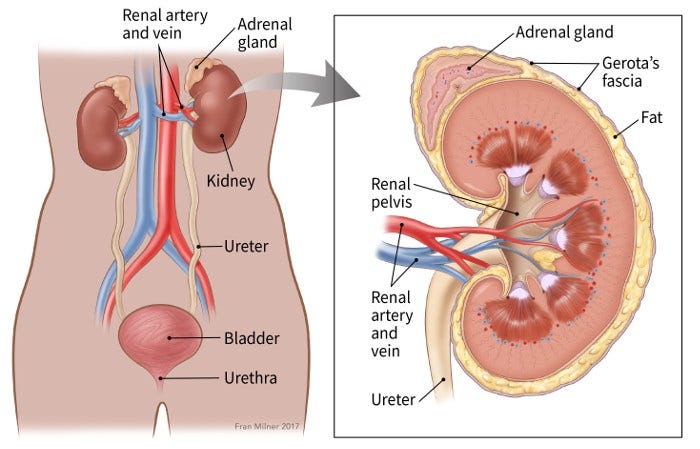
To understand these stages, it helps to know about some of the structures near the kidneys.
- Adrenal glands: Small glands that sit on top of each kidney. Like the kidneys, they are covered by Gerota’s fascia.
- Gerota’s fascia: A thin, fibrous layer of tissue that surrounds each kidney and adrenal gland.
- Renal vein: The main vein leaving the kidney, which connects it to the inferior vena cava.
- Inferior vena cava: The large vein that carries blood from the lower parts of the body back up to the heart.
Stages of kidney cancer
|
- The main tumor is no more than 7 cm* across and only in the kidney (T1).
- The cancer has not spread to nearby lymph nodes (N0).
- The cancer has not spread to distant organs (M0).
*7 cm = a little less than 3 inches
- The main tumor is larger than 7 cm* across, but it is still only in the kidney (T2).
- The cancer has not spread to nearby lymph nodes (N0).
- The cancer has not spread to distant organs (M0).
*7 cm = a little less than 3 inches
Stage grouping: T3, N0 or N1, M0
- The main tumor is growing into a major vein, such as the renal vein or the inferior vena cava, or it is growing into tissue around the kidney, but it is not growing into the adrenal gland or beyond Gerota's fascia (T3).
- The cancer may or may not have spread to nearby lymph nodes (N0 or N1).
- The cancer has not spread to distant organs (M0).
Stage grouping: T1 or T2, N1, M0
- The main tumor can be any size, but it has not grown outside the kidney (T1 or T2).
- The cancer has spread to nearby lymph nodes (N1).
- The cancer has not spread to distant lymph nodes or other organs (M0).
Stage grouping: T4, any N, M0
- The main tumor is growing beyond Gerota's fascia and may be growing into the adrenal gland on top of the kidney (T4).
- The cancer may or may not have spread to nearby lymph nodes (any N).
- The cancer has not spread to distant lymph nodes or other organs (M0).
Stage grouping: any T, any N, M1
- The main tumor can be any size and may have grown outside the kidney (any T).
- The cancer may or may not have spread to nearby lymph nodes (any N).
- The cancer has spread to distant lymph nodes and/or other organs (M1).
Other staging categories you might see
- T0: There is no evidence of a primary tumor.
- NX: Nearby lymph nodes cannot be assessed due to lack of information.
Prognostic factors for kidney cancer
Along with the stage of your cancer, your healthcare team can use other factors to help them understand your prognosis (outlook) and what treatments might work best. These prognostic factors could include your overall health, the results of lab tests, how the cancer cells look under the microscope, or other information.
There are several tools available that assign a person a risk group based on certain prognostic factors. Doctors use these tools to help predict the likelihood of a kidney cancer coming back after treatment. The tools might also be used to help decide treatment options.
|
The UISS can be used for localized kidney cancer or kidney cancer that has spread.
The prognostic factors for this tool are:
- The size of the main kidney cancer tumor
- Whether or not the cancer has spread to distant areas or lymph nodes
- Grade (how the cells look under the microscope)
- Performance status (a measure of how well a person can do usual daily activities)
Using these factors, people with kidney cancer can be placed into one of 5 groups. These risk groups suggest how likely it is that kidney cancer will return after surgery. They might also be used to help decide on treatment.
The IMDC can be used for renal cell carcinoma that has spread (metastasized).
This system uses 6 factors:
- High neutrophil count
- High blood platelet cell count
- High blood calcium level
- Anemia (low red blood cell count)
- Less than a year from being diagnosed to needing systemic treatment (chemotherapy, immunotherapy, or targeted therapy)
- Poor performance status (a measure of how well a person can do usual daily activities)
Based on these factors, a person is put into the low-risk, intermediate-risk, or high-risk group.
- Low-risk group: A person has none of the above factors.
- Intermediate-risk group: A person has 1 or 2 factors.
- High-risk group: A person has 3 or more of these factors.
A person’s risk group status can be used to help decide the best treatment options.
The MSKCC system might be used for renal cell carcinoma that has spread (metastasized).
This system uses 5 factors:
- High blood lactate dehydrogenase (LDH) level
- High blood calcium level
- Anemia (low red blood cell count)
- Less than a year from diagnosis to needing systemic treatment (chemotherapy, immunotherapy, or targeted therapy)
- Poor performance status (a measure of how well a person can do usual daily activities)
Based on these factors, a person is put into the low-risk, intermediate-risk, or high-risk group.
- Low-risk group: A person has none of the above factors.
- Intermediate-risk group: A person has 1 or 2 factors.
- High-risk group: A person has 3 or more of these factors.
A person’s risk group status can be used to help decide the best treatment options.
Other factors being studied
Other factors are being studied to understand prognosis in renal cell carcinoma (RCC). This includes studying markers on the cancer cells.
For example, in clear cell RCC, studies have found that certain markers and chromosome changes in the cancer cells may correspond to a worse prognosis. These markers are still being studied.
- Written by
- References

Developed by the American Cancer Society medical and editorial content team with medical review and contribution by the American Society of Clinical Oncology (ASCO).
American Joint Committee on Cancer. Ch. 60 - Kidney. In: AJCC Cancer Staging Manual. 8th ed. New York, NY: Springer; 2017.
Atkins MB. Clinical presentation, diagnosis, and staging of renal cell carcinoma. UpToDate. 2026. Accessed at https://www.uptodate.com/contents/clinical-presentation-diagnosis-and-staging-of-renal-cell-carcinoma on August 12, 2026.
Heng DY, Xie W, Regan MM, et al. External validation and comparison with other models of the International Metastatic Renal-Cell Carcinoma Database Consortium prognostic model: a population-based study. Lancet Oncol. 2013;14(2):141-148.
McNamara MA, Zhang T, Harrison MR, George DJ. Ch 79 - Cancer of the kidney. In: Niederhuber JE, Armitage JO, Doroshow JH, Kastan MB, Tepper JE, eds. Abeloff’s Clinical Oncology. 6th ed. Philadelphia, Pa: Elsevier: 2020.
Patard JJ, Kim HL, Lam JS, et al. Use of the University of California Los Angeles integrated staging system to predict survival in renal cell carcinoma: an international multicenter study. J Clin Oncol. 2004;22(16):3316-3322.
Last Revised: November 2, 2026
American Cancer Society medical information is copyrighted material. For reprint requests, please see our Content Usage Policy.
American Cancer Society Emails
Sign up to stay up-to-date with news, valuable information, and ways to get involved with the American Cancer Society.


